Pediatric Treatment Options for Nail Fungus
Find a Podiatrist Near You
Get same-day appointments with verified podiatrists. Insurance accepted.
Pediatric treatment options for nail fungus require a fundamentally different approach than treating the same condition in adults — because children are not simply smaller adults. Their bodies metabolize medications differently, dosing must be weight-adjusted rather than standardized, and the safety profile requirements are stricter when treating a healthy developing child for a non-life-threatening condition like onychomycosis.
Nail fungal infection in children is genuinely less common than in adults — prevalence estimates suggest roughly 0.3 to 2.6 percent of children under 18 have onychomycosis, compared to 10 to 14 percent of the adult population. But when it does occur, it causes the same structural nail damage, the same risk of spread, and the same impact on comfort and confidence as in adults — and it does require treatment rather than watchful waiting.
This guide explains how to recognize nail fungal infection in children, what the safe and evidence-based pediatric treatment options are, how dosing and monitoring differ from adult protocols, and what parents and caregivers can do to support treatment success and prevent recurrence.

Why Nail Fungal Infection Is Less Common in Children — and Why It Still Happens
Children’s relative protection against onychomycosis comes from several factors:
- Faster nail growth: Children grow nails significantly faster than adults — up to 3 mm per month for fingernails, with toenails growing faster than adult toenails proportionally. Faster nail growth means infected nail is replaced more quickly.
- Thinner nail plates: Thinner nails are easier for antifungal medications to penetrate, which is why topical treatments work better in children than in adults.
- Skin characteristics: The skin barrier and immune surveillance in children’s feet tend to resist dermatophyte colonization somewhat more effectively than aging adult skin.
Despite these protective factors, nail fungal infection occurs in children — particularly in the following situations:
Family exposure: Having an affected parent or sibling significantly increases risk. Shared bathroom floors, bath mats, nail tools, and footwear all provide transmission routes within households.
Communal activity: Participation in swimming, gymnastics, martial arts, team sports, and activities in shared locker rooms creates repeated fungal spore exposure.
Prior tinea pedis: Athlete’s foot (tinea pedis) in a child — which is more common than nail involvement — can spread to adjacent nails. A child with persistent skin scaling between toes should have their toenails examined.
Nail trauma: The same factors that create nail entry points in adults — tight footwear, sports-related nail impacts — apply to athletically active children.
Diagnosing Nail Fungal Infection in Children: Not Just by Appearance
Before exploring pediatric treatment options for nail fungus, an accurate diagnosis is essential — and this is arguably more important in children than in adults.
Multiple nail conditions in children produce nail changes that look like fungal infection but are not:
- Congenital malalignment of the great toenail — the toenail grows at an angle and appears thickened and dystrophic from infancy or early childhood, without fungal involvement
- Nail psoriasis — produces pitting, oil-drop discoloration, and lifting that resembles onychomycosis
- Nail trauma — from sports, tight shoes, or repetitive nail-to-shoe contact
- Alopecia areata affecting nails — rough, pitted nail changes
- Lichen planus — more common in adults but can affect children
Treating any of these with antifungal medication wastes months and delays appropriate care. Laboratory confirmation before starting pediatric treatment options for nail fungus is not optional — it is the standard of care.
Diagnostic approach in children:
- KOH preparation of nail clippings and subungual debris — the quickest and most accessible first test
- Fungal culture — confirms species identification, distinguishing dermatophytes (respond to terbinafine) from yeasts (require different coverage) or molds (may require itraconazole)
- In uncertain cases: PAS staining of nail biopsy specimen, with guidance from a pediatric dermatologist
Pediatric Treatment Options: A Conservative-First Framework
The hierarchy of pediatric treatment options for nail fungus follows a conservative-first approach — starting with the safest, least systemically-absorbed treatments and escalating only when clearly necessary.
Option 1: Topical Antifungal Medications — First-Line for Mild Infections
Topical antifungals are the appropriate first-line pediatric treatment options for nail fungus when the infection is:
- Confined to less than 50 percent of the nail plate
- Limited to one or two nails
- Involving the nail tip and body but not the nail matrix
- White superficial onychomycosis pattern (genuinely superficial infection)
Children’s thinner nail plates are a genuine advantage here — topical drugs penetrate more effectively in children than in adults, which partially explains why topical-only treatment is more often adequate in children.
Ciclopirox 8% nail lacquer (Penlac):
The most-studied topical antifungal for nail fungal infection in children. Ciclopirox has been used in pediatric cases and has a favorable safety profile with minimal systemic absorption. Applied daily to the nail surface, with weekly removal of accumulated lacquer before reapplication. Treatment courses typically run 6 to 9 months for toenail infections.
Efinaconazole 10% solution (Jublia):
Has been studied in children and adolescents. A published study in patients 6 to 16 years old showed mycological cure rates superior to vehicle control, with a favorable safety and tolerability profile. Its improved nail penetration properties (lower keratin binding affinity than ciclopirox) make it a strong topical option.
Tavaborole 5% solution (Kerydin):
Has also been evaluated in pediatric populations (6 to 16 years). Clinical improvement was demonstrated with daily application, and systemic absorption remained negligible.
Practical considerations for topical pediatric treatment options:
- Daily application for months requires caregiver involvement for younger children
- Allow the medication to dry before putting on socks
- Nail surface must be clean and free of nail polish before application
- Combine with nail trimming (short, straight across) to maximize drug contact with the nail surface
Option 2: Oral Terbinafine — For Moderate to Severe Infection
When topical agents alone are insufficient — infection involving more than 50 percent of the nail, matrix involvement (infection at the nail base), multiple nails infected, or failed topical treatment — oral terbinafine is the most effective and most evidence-supported oral pediatric treatment option for nail fungus.
Why terbinafine is the preferred oral agent:
- More clinical evidence in pediatric populations than itraconazole or fluconazole for dermatophyte nail infection
- Fungicidal rather than fungistatic — kills dermatophytes rather than just stopping their growth
- Favorable safety profile in children when appropriately dosed
- No known significant drug interactions in otherwise healthy children on no other medications
Dosing — this is where pediatric treatment differs critically from adult treatment:
Adult dosing (250 mg daily) cannot be applied to children. Pediatric dosing is weight-based:
| Child’s Weight | Daily Terbinafine Dose |
|---|---|
| Less than 20 kg | 62.5 mg daily |
| 20 to 40 kg | 125 mg daily |
| Greater than 40 kg | 250 mg daily (adult dose) |
Treatment duration for toenail infection: Most pediatric protocols recommend 6 to 12 weeks for toenail infection in children — shorter than the standard 12-week adult course is sometimes used, based on children’s faster nail growth rate, but the prescribing physician determines duration based on the individual case.
What forms are available: Terbinafine granules (125 mg and 187.5 mg packets) are available for pediatric use and can be mixed with food, making administration practical for younger children who cannot swallow tablets.
Liver monitoring: Baseline liver function testing before starting oral terbinafine is standard practice, even in children. Monitoring during the course is typically performed at 4 to 6 weeks. Children should be assessed for other medications that might interact via CYP2D6 (though the pediatric medication list is usually simpler than adults’).
When terbinafine is not appropriate:
- Confirmed Candida nail infection — terbinafine has limited yeast activity
- Confirmed non-dermatophyte mold infection — species-directed treatment is needed
- Known liver disease or significantly elevated baseline liver enzymes
Option 3: Oral Itraconazole — Second-Line or for Non-Dermatophyte Organisms
Itraconazole covers a broader spectrum than terbinafine, including dermatophytes, Candida species, and some non-dermatophyte molds. It is the appropriate oral agent when:
- Yeast (Candida) onychomycosis is confirmed
- Non-dermatophyte mold infection is confirmed
- Terbinafine is contraindicated
Pediatric dosing of itraconazole:
5 mg/kg/day (up to adult maximum), used either as continuous or pulse dosing. Itraconazole oral solution may be more appropriate than capsules for younger children, providing better and more consistent absorption.
The important drug interaction consideration:
Itraconazole inhibits CYP3A4. In children taking other medications, this interaction profile must be reviewed before prescribing. In otherwise healthy children on no medications, this is less of a clinical concern.
Monitoring: Liver function baseline testing and mid-course monitoring applies similarly to itraconazole as to terbinafine.
Option 4: Fluconazole — Limited Pediatric Use for Nail Fungus
Fluconazole is not considered a first-line agent for dermatophyte nail infection in children. It is used in some pediatric protocols for Candida nail infections, typically at weekly dosing (3 to 6 mg/kg once weekly). Evidence for fluconazole in pediatric onychomycosis is limited compared to terbinafine.
Option 5: Nail Debridement — Valuable Adjunct
Professional nail debridement by a podiatrist — trimming and thinning the infected nail using specialist instruments — is a safe and beneficial adjunct to pediatric treatment options for nail fungus.
Benefits in children:
- Reduces nail thickness, improving topical drug penetration (children’s thinner nails already penetrate more easily; any further reduction helps further)
- Removes subungual debris reducing fungal burden
- Provides immediate comfort if nail thickness was causing shoe pressure
- Allows clinical monitoring of nail condition at each visit
Debridement is safe throughout childhood and does not require anesthesia for routine thinning procedures.
What About Laser Therapy in Children?

Laser therapy for nail fungus (Nd:YAG 1064 nm and other systems) is occasionally discussed as a pediatric treatment option. The appeal is the absence of systemic medication exposure.
The honest assessment:
Published evidence for laser therapy in pediatric nail fungus specifically is extremely limited. General evidence for laser efficacy shows improvement in nail appearance but variable mycological cure rates compared to oral antifungal therapy. No specific safety concerns for laser applied to the nail have been identified in children, but neither has efficacy been established in pediatric populations through controlled trials.
Laser therapy in children should be discussed with a podiatrist or dermatologist on a case-by-case basis — not routinely recommended as a first-line pediatric treatment option when terbinafine is safely available.
Timeline for Pediatric Nail Fungal Treatment
Children’s faster nail growth is genuinely advantageous for treatment timelines:
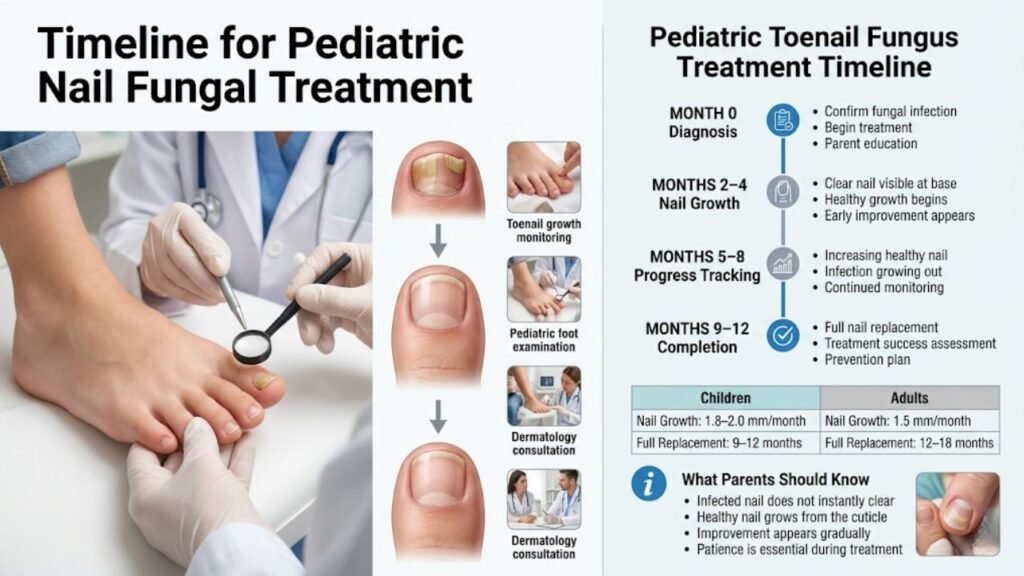
- Toenails grow faster in children — closer to 1.8 to 2.0 mm per month in children versus 1.5 mm in adults
- Full toenail replacement therefore takes less time — approximately 9 to 12 months in children versus 12 to 18 months in adults
- Results become visible sooner — clear new nail growing from the base is typically visible within 2 to 4 months of starting treatment
Managing expectations for parents:
The infected nail does not transform — it grows out. Clear new nail appearing at the base of the nail (near the cuticle) is the sign that treatment is working. Parents should be directed to watch the base of the nail for improvement, not the tip.
Prevention: Reducing Recurrence and Household Spread
After completing treatment, pediatric treatment options for nail fungus must be accompanied by prevention strategies — both to prevent the child’s infection from returning and to reduce spread within the household.
For the child:
- Wear protective footwear (flip-flops) in all communal wet areas — pool surrounds, gym changing rooms, school locker rooms
- Change socks daily and after sports
- Dry feet thoroughly after bathing
- Keep toenails trimmed straight across at a moderate length
- Do not share socks, shoes, or nail care tools with siblings or parents
- Treat any tinea pedis (athlete’s foot) promptly if it develops — it is the most common route back to nail infection
For the household:
- Identify and treat any other household member with onychomycosis — a fungal-infected parent’s feet on the bathroom floor is a continuous reinfection source for a successfully treated child
- Clean bathroom floor regularly with antifungal-containing cleaning products during active infection
- Replace shared bath mats during treatment
- Sterilize nail care tools shared within the household
Frequently Asked Questions About Pediatric Treatment Options for Nail Fungus
At what age can children receive oral antifungal treatment for nail fungus?
Oral terbinafine has been used in children as young as 12 months in clinical studies, with weight-adjusted dosing. There is no minimum age restriction in published guidelines, though younger children require more careful consideration and specialist involvement. Most pediatric cases requiring oral treatment are in school-age children.
How long does toenail fungus treatment take in children?
Thanks to faster nail growth, children typically see treatment outcomes in 9 to 12 months for toenails — somewhat shorter than the 12 to 18 months typical in adults. The oral treatment course itself (typically 6 to 12 weeks) is shorter than the full recovery timeline because the nail must physically grow out after the fungus is cleared.
Is it safe to use over-the-counter antifungal cream on a child’s infected toenail?
OTC antifungal creams (clotrimazole, miconazole) are designed for skin fungal infections like athlete’s foot, not for nail plate penetration. They are generally safe on children’s skin but are not effective for established nail fungal infection. For nail involvement, prescription-strength nail antifungals and proper diagnosis are needed.
Can nail fungus spread from a parent to their child?
Yes. Household transmission of onychomycosis is documented. Shared bathroom floors, bath mats, nail tools, and footwear provide routes for dermatophyte transfer. In households where a parent has active onychomycosis, children face elevated exposure risk — and treating the parent alongside the child reduces reinfection risk.
What happens if nail fungus in a child is left untreated?
Unlike in elderly or diabetic adults where untreated nail fungus carries serious complication risks, nail fungal infection in otherwise healthy children progresses slowly and rarely causes medical emergencies. However, untreated infection typically spreads to more nails over time, can spread to siblings and family members, and may cause discomfort from thickened nails in footwear. Early treatment is preferable to extended monitoring.
Summary
Pediatric treatment options for nail fungus follow a conservative-first approach, starting with confirmed diagnosis and moving from topical antifungal therapy for mild infection through weight-adjusted oral terbinafine for more established or severe cases. Children’s faster nail growth rate and thinner nail plates provide genuine treatment advantages — better topical penetration and faster nail replacement — that make pediatric treatment outcomes generally more favorable than in adult populations when appropriate treatment is used.
The essential steps for any case: confirm the diagnosis with laboratory testing before starting treatment, use weight-adjusted dosing for oral medications, include baseline liver function monitoring, perform nail debridement as an adjunct when appropriate, and implement household and environmental prevention to protect both the treated child and other family members.
With accurate diagnosis, appropriate treatment selection, and consistent application or adherence, pediatric nail fungal infection is highly manageable — and children’s natural biological advantages in nail growth make clearance faster and more achievable than the same treatment in adults.
Struggling to get an appointment?
We help patients in your area bypass clinic waitlists by instantly finding verified podiatry doctors who accept their insurance.